Friday, March 11, 2016

Bacterial translocation in surgical patient

Bacterial translocation  in surgical patients


       Recent  years have seen an increasing recognition of the fact that the gastrointestinal tract has  functions other than simply the digestion and excretion of foodstuffs. The  gut is also a metabolic and immunological organ that serves as  a barrier against living organisms and antigens within its lumen. This  role is termed  'gut barrier function.' The fact that luminal contents in the caecum have a bacterial concentration of the  order  of 10 organisms/ml of faeces, whilst portal blood and mesenteric lymph nodes are usually sterile, dramatically illustrates the efficacy of this barrier function.

        
          The idea that the alimentary tract, teeming with its own bacterial flora, could represent a source of sepsis under  certain  conditions has interested  clinicians  for many years. This theory , usually referred to as the 'gut  origin of sepsis' hypothesis, is not new. In the  late 19th century, the idea  evolved that peritonitis could result  from the passage of bacteria from  organs adjacent to the peritoneal cavity. In Germany this was referred  to as durchwanderungs-peritonitis, literally  translated as 'wandering through peritonitis.' In 1891 and 1895, two seperate investigators hypothesised that viable bacteria could pass  through the  intact gut wall in vivo. It was Berg and Garlington in 1979 who defined this phenomenon  as 'bacterial translocation.'


       'Translocation ' is used to describe the passage of viable resident bacteria from the gastrointestinal tract  to normally  sterile tissues such as the mesenteric lymph nodes and  other internal  organs. The term also applies to the  passage of inert particles and other macromolecules, such as lipopolysaccharide  endotoxins, across the intestinal  mucosal  barrier.


Saturday, February 20, 2016

BONE METASTASES

Bone  Metastases


     Preoperative  transarterial embolization of hypervascular bone metastases, most commonly  renal metastases, is a very useful and helps reduce  preoperative blood loss and surgical morbidity. As a technique this was first  described  by Feldman et al and there have been a number of subsequent studies with favorable results . Barton et al reported 500-1500 ml intraoperative estimated blood loss (EBL) in embolized patients as compared to 2000-18500 ml if no embolization was performed . Further, even  partial devascularization of the lesion is beneficial in reducing estimated  blood loss although complete  devascularization is ideal.

     Tumor  vessels can originate  directly from a main artery or from distal  2nd or 3rd order branches. Embolization of the  former carries a higher risk of embolising down the main artery and the latter comes with cannulation  problems with smaller calibre arterial branches. Successful cannulation of the smaller branches gives the freedom  of aggressive embolization whilst proximal tumor  branches require extra care.

     The technique involves vascular access via a suitable artery depending on the tumor location.  Initual angiography  should include detailed  demonstration of all  the feeding branches. The tumor  arteries should be cannulated and  catheter positioned beyond any major  arterial branches. Embolization is usually performed using polyvinyl alcohol (PVA)  particles. The particle size should be appropriate to the size of the arterial branches embolised. Other  agents including  gelatine  sponge and coils have been  used.


      Transarterial  embolization of bone tumors is usually  safe with a few potential  complications. Post  embolization syndrome is not unusual  and should be considered for  planning  both the embolization and the surgical procedure. A number of these  bone lesions involve  the appendicular  skeleton and  hence embolization down the femoral or brachial arteries can result in ischemic  symptoms. Similarly   skin necrosis  and nerve palsies have been reported.

DNA METHYLATION AND EPIGENETIC GENE SILENCING

DNA  METHYLATION AND EPIGENETIC GENE SILENCING


     DNA methylation is a reversible chemical modification of the cytosine in the CpG islands  of promoter sequences, catalyzed by a family of DNA methyltransferases. DNA  methylation does not change  the genetic information but it just alters the readability of the DNA  and results  in the  inactivation of gene by  subsequent transcript repression.  CpG island  are the regions  in DNA  that  contains  many adjacent cytosine and guanine nucleotides. The ''p '' in CpG  refers to the phosphodiester bond between  the cytosine   and  the guanine. These islands  occur  in  approximately  40% of the promoters  of human  genes. These  islands occur  in approximately 40%  of the promoters  of human genes. DNA methylation  plays  a critical  role in the control  of cellular  process  including  embryonic development , transcription, X- chromosome inactivation and  genomic imprinting. DNA  methylation occurs in the C5 positions of cytosines that precedes guanines and  are called dinucleotide CpGs. The CpG dinucleotides are not found frequently throughout the human genome and present 20 % of its  expected frequency. But approximately half of the human gene promoter regions have CpG rich areas of 0.5 to 2 kb in length. In which CpG
dinucleotide frequency are higher than expected . These CpG rich areas are often known  as CpG islands. . The majority (94%) of CpG island  remain  unmethylated  in normal cell. But particular subgroups of promoters CpG are  methylated  such as tissue  and germ line specific genes. In general , CpG  island methylation causes gene silencing. The  methylated CpG  island  also recruit   histone deacetylases  and other factor involved  in transcriptional silencing .  In activation  of tumor suppressor genes through  hypermethylation of CpG islands within promoters regions is a major event in carcinogenesis. Hypermethylation of CpG  islands within promoter regions  is a major  event in  carcinogenesis . Hypermethylation of CpG  island also has silencing effect on miRNA  in cancer. Micro RNA are short , 18-22  nucleotide, noncoding RNas that
regulate many cellular functions including cell proliferation, apoptosis and differentiation by silencing specific target  genes through translational repression or mrNa degradation.

COMPOSITE TISSUE ALLOTRANSPLANTATION

COMPOSITE  TISSUE  ALLOTRANSPLANTATION  


        After the report of the first microvascular tissue transfer  the free transfer of autologous tissue became the  mainstay for  treatment  of complex soft tissue defects and with reimplantation  of the  hand and digits, the modern era of replantation in reconstructive  surgery began in the  1960.
    
        Composite tissue allotransplantation (CTA)  is a term that includes transplantation of multiple tissues of ecodermal and mesodermal  origin. It  involves simultaneous transplantation  of tissue  components  involving  skin, muscle, nerve bone and tendons. Transplantation of hand is one of the best examples of CTA concept and it has  brought the  attention  of the  scientific  community and the public  to this new field of transplantation. The growth of solid organ transplantation also parallels the emergence of newer immunosuppressive drugs.

       The first hand transplant was performed in Lyon France in 1998, with eventual graft loss due to noncompliance with immunosuppression. The clinicopathological  freatures of rejection were largely confined to skin with milder involvement of muscle   and tendon and sparing of bone and joints.

     Louisville School of Medicine  in United  States has taken lead  in hand transplant surgery in the United  States. Of the approximately 30 hand transplants done worldwide, 3 have been done in Louisville. A hand  transplant protocol by the University  was drawn up. Patient recruitment  is rigid. The transplant protocol by the University  was drawn up. Patient  recruitment  is rigid. the pretransplant  psychiatric evaluation  screening tests are similar to solid organ transplantation  and include routine  blood work out. ABO  type, cancel reactive antibody, infection screen , chest X-ray, cardiac evaluation, etc .

      Decreased donor has to meet the standard criteria for determination of brain death. Donation after cardiac death is not  considered. All donors were from the jurisdiction of the  local organ procurement organization. ABO blood group compatibility and a negative  crossmatch with the recipient was necessary. Absolute contraindications included active  intravenous drug use. A detailed evaluation of the limbs of the potential donors included range of motion in all joints and absence of arthritis.


     The details  of the donor procedure is described briefly. A circumferential incision is made around the  distal arm with identification of underlying  veins and cutaneous  nerves. another longitudinal incision is made along  the medical side of the arm over the brachial vessels  to enable cannulation for cold perfusion of the limb with the University of Wisconsin  solution.

        The sequency of tissue repair proceeds in the following order: bony fixation, arterial revascularization, vein repair, tendon repair and nerve  repair. All  patients  received  heparin for 48 hours postoperatively.

       Immunosuppression   was induced with basiliximab , tacrolims, MMF  and steroids, The digits were fixed in metacarpophalangeal  fiexion.  The   wrist was in a dynamic brace. a transcutaneous electrical  nerve stimulation unit to decrease pain and  electric muscle stimulator were  used throughout the rehabilitation course. Skin biopsies were performed to monitor rejection.

       In  Malaysis, an upper extremity transplantation was performed at the level of the shoulder on a 28 day old neonate  born with congential absence of one arm.  The identical  twin had fatal brain anomaly and was the donor of  the limb. The  transplanted limb grew at the same rate as the native limb and after 7 years was  functional. One major controversy surrounding CTA is the  toxicity of immunosuppression with an increased risk of cancer, organ failure and opportunistic infections.

      Many other tissues have been successfully transplanted to restore tissue loss from trauma or tumor. Simultaneous and sequential abdominal wall transplantation  coincident with intestinal transplantation has been reported from University of Miami. A 40- year- old man received the  first  successful human laryngeal transplant in 1998. A human leukocyte antigen matched  laryngopharyngeal complex including  thyroid,prathyroids and five rings of trachea were transplanted  along with   anastomosis of both superior and one of the recurrent laryngeal nerves.

       At a follow- up of more than 7 years, the patient had excellent  function, normal swallowing and good phonation. Other workers have reported 13 laryngeal transplantations with 90 percent graft survival at 2 years using immunosuppression similar to renal transplantation . Patients with  severe disfigurement of face not amenable to reconstruction are likely to benefit from partial face transplantation. The first  facial transplant was in a 38- year- old woman, disfigured by a severe dog bite who received a  central and lower  facial transplant in 2005.  A sentinel skin graft was placed in the left inframammary area to monitor rejection.  Sensitivity to  light touch and temperature returned by 6 months , whereas  motor recovery allowing complete mouth closure was achieved at 10 months . Despite two episodes of acute rejection and renal  dysfunction requiring cessation of tacrolimus, the patient is satisfied with aesthetic result and  is maintained on sirolimus, MMF and prednisone.

Wednesday, January 6, 2016

BASIC ACCOUNTING CONCEPTS

BASIC  ACCOUNTING  CONCEPTS

     Accounting  is based on certain assumptions.  These assumptions are known as basic  accounting  concepts. Those basic accounting concepts are as follows.


  • Business entity concept : This concept states that the business and its owners are two separate and  distinct  entities. According to this concept, all transactions of the business have to be accounted for from the viewpoint of the business and not from the view point of its owners. The distinction between the business  and its owners is essential in order to ascertain the true picture  of a business.  If the two are not  separated for accounting purposes, the transactions of the busiess will be mixed up with the personal  transactions of its owners  and the true picture of the business can not obtained.


  • Going  concern concept : This concept implies that a business has an indefinite life and it exists for a long period of  time. All business tranactions are performed and recorded from this point of view. The long- term expenditures such as the purchase of land, building and  machinery that the business makes are recorded  in books of  account assuming  that  it will exist and run for a long period  of time.  Their  costs and not the current resale values are recorded spreading over their estimated working  lives. Therefore, the balance sheet always shows fixed assets at cost after subtracting the depreciation.


  • Money measurement concept :  This concept assumes that only those business tranactions which are measured and expressed in monetary terms have to be taken into account. It is so assumed  because money provides a common measure for different goods, services, assets and  liabilities. This concept also assumes that  monetary units such as 'rupee' are stable units in value , but this assumption may not be  true in reality. Therefore, in spite of a decrease in the purchasing power of money, accounting  is performed assuming that the value of money is stable over time.


  • Accounting period concept : The accounting period concept implies that for the purpose of reporting financial information, the whole life of the  business is divided into imaginary  time- intervals. Each time interval is called  an accounting period which is normally  of one year. In Nepal, it begins on the 1st of Shrawn  every year and ends  on the last day of Asad the next year. At the end of each accounting  year, financial statements are drawn to ascertain the  profit  or loss and the financial position of the  business, and are reported  to their users such as owners, managers and creditors.

  • Revenue concept-This concept is also called realization concept. The concept states that revenue is assumed  to be earned when it is realized . According to the concept, revenue is realized when goods  are transferred to the buyers  and services are provided to the clients for  cash, or for assets or in  anticipation of  realizing the value of sales on a future date. It is not  necessary that the revenue must be realized in cash.  Besides , revenue is  earned in the period when it is realized. However, revenue  realized is always net  of goods returned from the customer  and bad debts.


  • Cost concept :  This concept implies that the cost of anything  such as a service or an asset is recognised when it is incurred and not when cash  is paid for it.  According to the concept, the  cost is assumed to be incurred when the service or the asset is used to generate  revenue .  Besides, the concept assumes that  the asset is taken into account at the cost of its purchase and not at its market value. This concept , however does not mean that the cost of purchase appears in the books every year. Since an asset  has a limited life, its cost  is written  off every year over its life. Thus, the books show the asset at the purchasing  cost less its depreciation up- to- date.


  • Matching concept: This concept provides guidelines as to how the profit or loss of a business should be determined. The  concept , therefore, states that  revenue earned in a period has to be matched with  the expenses incurred  in the same period so as to find  out the true  profit or loss  of the business. While matching the expenses with the revenue , the latter should be realized first and then only the expenses  relating to the revenue should be recognized . Any expense or revenue of the previous  or the next year  should not be matched with those of this  year. If they are matched, the true profit or loss can not be  ascertained.


Epigenetics and Cancer


Epigenetics and  Cancer


INTRODUCTION
  
        
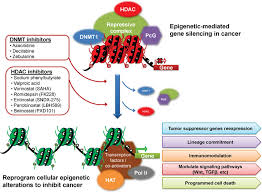
         Epigenetics  is a rapidly evolving study of molecular genetics and biological research. The advancement in the understanding of different  biological activity like DNA methylation, chromatin structure, transcriptional  activity and histone modification has resulted in the development  of epigenetics. Epigenetics changes influence gene transcription  without alteration in the DNA  sequence. The term '' epigenetics was first used by Conrad  Waddington in 1939 to describe ' the causal interaction between the genes and their products, which bring  the phenotype into being.'' In  present  era the term  epigenetics has broadened to include heritable and  transient / reversible changes in gene expression that is not accompanied  by a change in the DNA  sequence. There are two type  of major of major  epigenetic  modification: those occurring  at the DNA level (DNA methylation) and  those occurring at the chromatin  level ( chromatin  remodeling). DNA  Methylation is an  enzyme driven chemical change to the DNA  sequence that most commonly occurs at CpG dinucleotides.  Chromatin remodeling  occurs via modification of the histone residues  by enzymes  primarily  on  the N- terminal  tails and ultimately effects  the interaction  of DNA  with chromatin modifying  proteins. Both DNA methylation and histone modification are associated with silencing critical  tumor suppressor genes and activating oncogones involved in cancer.


       Most  of the traditional  molecular studies on cancer are on identifying the genetic mutation or on tumor suppressor gene. Recently, more studies are now focused in discovering new biomarkers  that are epigenetically silenced in early carcinogenesis.  It  is also seen that almost half of the  tumor suppressor genes that  causes familial  cancer through mutations can  also get inactivated with  promoter hypermethylation  in sporadic  cancer. Increasing  evidence suggests  that epigenetic changes  play a key role in  cancer development.

          
          The various  genetic  markers has been used for the early  tumor detection, prognostic prediction and explaining  the genetic pathway of carcinogenesis. But the epigenetics marker has  gained popularity in recent year particularly the promoter hypermethylation which has various  advantages over  a genetic marker.  First promoter hypermethylation is  much more common than genetic alteration  in cancer.  Second promoter hypermethylation occur in the same defined region of that gene  in  all  form of cancer in comparison to wide  range of mutational  variations occur within a specific  gene. Thus epigenetic detection of promoter                                                                                             hypermethylation  will be both efficient and 
                                                                       cost- effective method of tumor detection.   


DNA METHYLATION AND EPIGENETIC GENE SILENCING

DNA  METHYLATION AND EPIGENETIC GENE SILENCING


     DNA methylation is a reversible chemical modification of the cytosine in the CpG islands  of promoter sequences, catalyzed by a family of DNA methyltransferases. DNA  methylation does not change  the genetic information but it just alters the readability of the DNA  and results  in the  inactivation of gene by  subsequent transcript repression.  CpG island  are the regions  in DNA  that  contains  many adjacent cytosine and guanine nucleotides. The ''p '' in CpG  refers to the phosphodiester bond between  the cytosine   and  the guanine. These islands  occur  in  approximately  40% of the promoters  of human  genes. These 
islands occur  in approximately 40%  of the promoters  of human genes. DNA methylation  plays  a critical  role in the control  of cellular  process  including  embryonic development , transcription, X- chromosome inactivation and  genomic imprinting. DNA  methylation occurs in the C5 positions of cytosines that precedes guanines and  are called dinucleotide CpGs. The CpG dinucleotides are not found frequently throughout the human genome and present 20 % of its  expected frequency. But approximately half of the human gene promoter regions have CpG rich areas of 0.5 to 2 kb in length. In which CpG dinucleotide frequency are higher than expected . These CpG rich areas are often known  as CpG islands. . The majority (94%) of CpG island  remain  unmethylated  in normal cell. But particular subgroups of promoters CpG are  methylated  such as tissue  and germ line specific genes. In general , CpG  island methylation causes gene silencing. The  methylated CpG  island  also recruit   histone deacetylases  and other factor involved  in
transcriptional silencing .  In activation  of tumor suppressor genes through  hypermethylation of CpG islands within promoters regions is a major event in carcinogenesis. Hypermethylation of CpG
  islands within promoter regions  is a major  event in  carcinogenesis . Hypermethylation of CpG  island also has silencing effect on miRNA  in cancer. Micro RNA are short , 18-22  nucleotide, noncoding RNas that regulate many cellular functions including cell proliferation, apoptosis and differentiation by silencing specific target  genes through translational repression or mrNa degradation.

Tuesday, December 1, 2015

Laparoscopic


          Laparoscopic   Management   OF   Large   Hiatus   Hernia

INTRODUCTION


   The Management of large hiatal hernias is difficult and their operative repair can be technically challenging . The concept of a large  hiatal  hernia, however, has not been clearly defined. They have been classified by various  authors according to whether the hiatal defect  is larger or  smaller  than 5 cm and or / or their  contents. Aly et al considered hiatal hernias to be large when more than 50 percent  of the stomach has migrated into the chest.  Andujar  defined  it as the presence  of more than one- third of the stomach in the thoracic cavity. Carlson et al in his study has  defined  hiatal  hernias to be large if the  hiatal defect is larger than 8 cm which was later  modified to 5-6 cm. We consider paraesophageal hernias to be large  when more than half of the stomach has migrated into the chest or if the hiatal defect is larger than 5 cm in size.
    
    Hiatal hernias are classified into type I to IV depending on the position of the gastroesophageal junction in relation to the diaphragmatic  hiatus. According to the conventional classification, type III and type IV can be considered to be large hernias. Type III hernias, which is a mixed sliding and paraesophageal hernia (PEH)  occurs predominantly in the elderly population . The end stage of a hiatus hernia  is an intrathoracic stomach in which the whole stomach  migrates into the chest by rotating 180 degrees along its longitudinal axis with the caedia and the pylorus as fixed points  and includes other organs including colon, omentum, small bowel , liver and spleen (TypeIV).
   
     Surgical correction of large hiatal hernias is indicated because of unsatisfactory outcomes after long- term medical  management and potentially disastrous consequences of gastric incarceration or volvulus  in large paraesophageal hernias. Fundamental steps involved in large hiatal hernia repair include a tension free reduction of the esophagus  and the stomach into the abdomen with complete excision of the hernial sac, reapproximation  of the hiatus, and subdiaphragmatic  fixation of the stomach, with many authors advocating the additional of an antireflux procedure.


     Recurrence rates after laparoscopic surgery is a controversial and unresolved  issue. A few early studies have shown alarmingly  high recurrence rates. Some possible patient related and procedure  related mechanisms are  in appropriate postoperative activity  of the patient immediately after surgery, inadequate excision of the sac, inadequate mobilization of the esophagus, inadequate crural closure secondary to widely spaced crura sutured  under  tension , or a postoperative rupture of crurorraphy due to continuous excursion of the diaphragm.
   
     After complete reduction of all the hernial contents, the necessity of complete excision  of the  hernial  sac cannot be understated. IN  earlier series recurrence rates of up to 20 percent have been  reported after inadequate excision  of the hernial  sac . Although  sac removal is tedious and difficult,it is one of the most  crucial  steps of large paraesophageal  hernia repair. If  circumferential  reduction of the sac  is not done and a portion  of the  sac of new  hernia formation has been  practically  left behind. Fluid collections in the unresected sac leading to postoprative dysphagia have also been reported in literature.
   
     A number  of methods have been adopted to reduce the risk of postoperative recurrences and include the use of Teflon pledgets to prevent crural sutures from cutting through, complete detachment of the sac from the hiatus and mediastinum, complete excision of the sac, adequate mobilization of the esophagus and use of mesh cruroplasty in patients with a large hiatus hernia to achieve a tension free hiatal.


SURGICAL PRINCIPLES


    Although the need for surgical repair is undebated, controversies exist concerning the best surgical  approach  whether open or laparoscopic, the presence of short esophagus and the need for an esophageal lengthening procedure, crurorraphy or a tension free mesh repair, subdiaphragmatic  fixation of the stomach , the need for an antireflux procedure, whether total or partial fundoplication and the indication for prosthetic  reinforcement of the hiatus.

GALLSTONES

                                           GALLSTONES


      Biliary tract  disease is the second  most common  non- obstetric  surgical problem, though it affects only 1 in 1600  to 10000 pregnancies. Cholelithiasis has been documented in 10  percent  of pregnancies and  cholecystitis reportedly affects  0.1 percent  of pregnant patients.
        Pregnancy related  physiological  changes : a. Progesterone causes smooth  muscle relaxation  and  a decrease  in gallbladder tone.  Weakened  contractions and  decreased  emptying  lead to increased  gallbladder  volume  during  fasting  and after eating. In  turn, biliary  stasis  contributes  to cholesterol  crystal sequestration ,  theoretically leading to the  formation  of sludge and stones. b. Elevated  estrogen levels during  pregnancy may further  increase the lithogenicity  of bile. c. Lower  gallbladder  ejection  fractions  and increasing  parity seem  to increase the risk of  sludge formation. A high pre-pregnancy body mass  index  also  may increase the  risk  of sludge  formation. Despite these  physiologic changes, it is unclear if  pregnancy increases  the incidence of gallstones  and  cholecystitis . In  a German  population  study looking  at 1111 females, current pregnancy and the number of prior pregnancies were not associated with an increased  risk.

       The clinical presentation of acute  cholecystitis is similar  to the non- pregnant patient. The pregnant - patient who has right upper  quadrant  tenderness  should undergo ultrasound  evaluation  first because it is  noninvasive and quickly obtained.  MR cholangiography can be suspected  but not demonstrated on  ultrasound.  Symptomatic  cholelithiasis often is managed initially with  a conservative approach,  delaying elective cholecystectomy until after delivery. If conservative  management fails, or if repeated hospitalizations are required, especially  in the same  trimester, cholecystectomy is indicated. Recent studies have  shown, earlier surgical intervention  for biliary tract disease in pregnancy is safe with reduced hospital stay, reduced use of  medications, lower rates  life- threatening complications and lower preterm deliveries. The  laparoscopic cholecystectomy  has been performed safely in all trimesters. The use of an  open  technique for entry, insufflations to 12 mm Hg, and  maintaining a left lateral decubitus  position minimize risk to the fetus and  help maintain adequate placental blood flow during  surgery.
        Patients presenting with acute cholecystitis and symptomatic choledocholithiasis  during pregnancy  should be considered  in a higher  risk  category. If  complications such  as cholangitis or gallstone  pancreatitis develop, maternal mortality  approaches 15 percent, and fetal loss occurs in 60 percent of cases . 


        Surgical approaches  include open cholecystectomy with choledochotomy  or laparoscopic  cholecystectomy with ERCP (endoscopic retrograde cholangiopancreatography ) with sphincterotomy  for  stone extraction or stent placement has been shown  to be  safe during pregnancy.  Although  not routinely recommended, intraoperative  cholangiography   is safe  after fetal organogenesis is complete  and does not increase the risk   of preterm  labor or adverse fetal outcomes.

APPENDIX

                                                      APPENDIX


     Appendicitis is the most common non- obstetric surgical complication and the most common gastrointestinal disorder  requiring  surgery during pregnancy. It accounts  for 25 percent of surgeries for non- obstetric  indications in  pregnancy and complicates every  1 in 1500 to 2000 pregnancies. The incidence of perforated  appendicitis in pregnant women is 43 percent compared to 4-9 percent in the non- obstetric  population.  This increased  incidence may be due to delay in diagnosis and reluctance to operate in pregnancy. Maternal and fetal morbidity and  mortality correlate with perforation and  its associated complications. Uncomplicated appendicitis has a 3-5 percent  fetal loss rate with negligible maternal mortality. Appendix perforation, however, is associated with a 20-35 percent fetal loss rate and 4 percent maternal mortality. Appendix  perforation , however , is associated  with  a 20-35 percent  fetal  loss rate and 4 percent  maternal  mortality. Maternal  mortality rates have  dropped  significantly in the  recent  years with prompt surgical  intervention , newer antibiotics and  surgical  techniques. 

      The preterm contractions  caused  by  uterine irritation from perforation peritonitis result in preterm delivery in 5-14 percent. This incidence is similar between  open  and laparoscopy. In the  first trimester the  appendix remains in its  normal anatomic  position. The appendix  undergoes progressive displacement cephalad  and laterally with advancing pregnancy. After 24 weeks gestation, the  appendix is shifted superiorly  above the right iliac crest , and the tip of the appendix is rotated  medially toward the uterus. By  late pregnancy, the appendix may be closer to the gallbladder than MCBurney's point, occupying the right upper quadrant . This change may alter the location of the pain, making diagnosis difficult. As the  peritoneum is displaced  from the appendix  and cecum by the growing uterus, the increased separation of  the visceral  and parietal peritoneum  decreases  the somatic  sensation of pain and compromises the ability to  localize pain  on examination. The enlarging uterus interfere with the ability  of the omentum and bowel to wall off the inflamed appendix.  Diffuse peritonitis from perforation is  facilitated by this inability of the omentum to isolate the infection. The appendix  returns  to its normal  position by the tenth postpartum day. However, modern clinical experience does not confirm this assertion, with recent studies demonstrating  that the most frequent  location of pain  remains in the right lower quadrant, regardless of trimester. 
               

     Symptoms of appendicitis often  are confused with normal  pregnancy related conditions, particularly in the third trimester. Pain in the right lower quadrant is the most  common and reliable symptom  of appendicitis along with the usual features of appendicitis. Rectal  and pelvic tenderness may not be present when the appendix  is displaced by the uterine enlargement. Leukkocytosis is normal in pregnancy  and so not a good  indicator. Ultrasound Scan is useful  in the first  and second trimester. MRI is safe in pregnancy . CT  Scan should be reserved for cases where Ultrasound and MRI are non- diagnostic. Despite reluctance to operate on a pregnant patient, immediate surgical  intervention is indicated when a  diagnosis of appendicitis is made. The choice of surgical procedure is  based on uterine size and experience  of the  surgeon.  The only indication  of delay  is active labor, and in these  cases the surgery is performed immediate  postpartum.
Add caption


      Diagnostic and operative  laparoscopy  is reasonable  before 20 weeks gestation  and is as safe as open surgery. When  performing  laparoscopy  open entry(Hassan)  is preferable to avoid inadvertent veress or trocar  entry into uterus. Trocar placement  needs to be changed according  to the  size of the uterus. Beyond the late second trimester, laparoscopy  becomes more technically challenging . Appendicitis is confirmed in 36-50  percent of cases. Accuracy of diagnosis  in the  first trimester is greater.  A higher false positive rate is acceptable  in pregnant women, because  any delay in diagnosis may compromise maternal and fetal  well - being .

Tuesday, November 3, 2015

THE DIABETIC FOOT


    An  important  underlying  cause leading to diabetic foot problem is neuropathy. Sensory  neuropathy  leads  to a loss of  protective  sensation. Foot  trauma  is unrecognised and leads to ulceration. The ulceration is often the portal of entry for bacteria, leading to cellulites and/ or abscess formation. Motor neuropathy can lead to asymmetric  muscle atrophy, foot deformity (equines deformity) and altered  biomechanics. This  leads to areas of high pressure during standing or walking and repeated  trauma  that may go unrecognised  because of sensory deficit. Autonomic neuropathy results in loss of sweating and dry skin that leads to cracks and  fissures and a portal of entry for bacteria. Diabetes is also associated with an increased risk of peripheral arterial disease and it can be a major factor in non- healing of foot ulcerations.
 
     Diabetic patients can have significant foot infection, with much less pain and no pronounced systemic inflammatory response. A high index of suspicion is therefore required to diagnose foot infection in patients with diabetes.
                                                   

     The skin of the foot is a highly specialized organ. The plantar skin consists of a complex array of fascia, fibrous septae and tangential shearing forces that occur during walking. The dorsal skin is bound to the underlying extensor retinaculum.  Infection tracks along fascial  planes and tendon sheaths. The location of a diabetic foot wound will usually lead surgeon to the underlying cause. An  ulcer at the posterior border of the heel is usually the result of chronic pressure from prolonged contact with bedding, friction from rubbing against rough bed sheets and lack of elevation. An ulcer about the plantar foot is almost always due to i) excessive pressure and time between the foot and the contact surface, ii) neuropathy and iii) deformity of the foot ( equines contracture). Understanding  the underlying cause will allow an effective wound care. The single best means of reducing pressure on the sole of the foot  is to employ non- weight bearing of the involved  limb through use of crutches or walker. This  may not always be practical but effort should be made to emphasize compliance. Use of standard off- loading shoes are also recommended.
   
    Pain in a neuropathic  foot is usually related to an underlying infection. After a thorough surgical preparation, in the emergency room, to remove debris and allow proper evaluation, the wound is probed to determine its depth and tissues involved. Osteomyelitis should be considered if the wound is deeper than the dermis layer. Most patients with diabetes who present  with a severe foot infection have chronically poor glycemic  control, chronic anaemia, poor nutrition and deficient clinical care. Therefore, laboratory studies and necessary management is essential  before embarking on active treatment.


    An important initial  step in treating limb threatening diabetic foot infection is to perform a timely and adequate surgical  debridement. This entails surgical excision of all nonviable and/ or infected  tissue. The plantar spaces are opened by longitudinal incisions with division  of plantar fascia. When pus is present in flexor tendon sheaths, these are opened and drained. In order to appropriately evaluate the viability of the soft tissues and the underlying structures, surgical  debridement should be performed without the use of a tourniquet. If there is exposed bone or suspicion of osteomyelitis, cultures are obtained of this tissue. Wound is irrigated and meticulous hemostasis achieved. Most diabetic foot infections are treated with an empirically selected antibiotic regimen until cultures and sensitivity are available . In a limb threatening infection or osteomyelitis, intravenous therapy should be initiated and followed if possible by oral agents. The use of topical antibiotics has a limited place as may produce the development of resistant strains of colonized surface bacteria.

    A patient with diabetes may not give the typical history of claudication because of associated  neuropathy or lack of activity. It is therefore  important to evaluate the limb for peripheral arterial disease even  in the absence of symptoms. If pedal pulses are not clearly palpable, further vascular studies are indicated. An ankle- brachial index (ABI) should be obtained.

      There is a close association between peripheral arterial disease and coronary disease making then both a high risk for a traditional open bypass procedure. The endovascular options include percutaneous angioplasty  with or without a stent . These procedures cab be performed under local  anaesthesia and sedation and with a high rate of limb salvage .

      The standard treatment of diabetic foot ulcer includes adequate off- loading of weight, frequent ulcer debridement , wound care, treatment of infection and revascularization of ischemic limb. This standard  care in many controlled trials  has resulted in healing of a number of foot ulcers.  However, newer therapeutic  modalities that can improve healing also need to be explored.

     Despite recent advances in surgical and radiologic vascular techniques, a fair number of patients with critical limb ischemia are not eligible for a revascularization procedure.  This is because of anatomic location of the lesion, the extent of the disease or extensive co-morbidity . No  effective pharmacologic  therapy is available  and amputation is often  the only option left.  The cost of managing a patient after amputation has been estimated to be almost  twice that of a successful limb salvage . Therefore, exploring new strategies for ischemic limbs is of major importance.  Bone marrow derived progenitor cells have been identified as a potential new therapeutic target.

    Normal wound healing is a intricate process involving various  cell types, coordinated processes, and complex signaling  interactions.  In a diabetic wound , many of these  responses to inflammatory mediators, matrix production, angiogenesis, and wound contraction have all been  poor and contribute to delayed  healing of a diabetic wound.

     Cell - based therapy is an attractive approach for the treatment of wounds with multiple impairments. Mesenchymal stromal  cells (MSCs) are the multipotent cells derived from stroma  of bone marrow  and other tissues. The local delievery  of  MSC to a diabetic wound might  correct wound healing impairment both indirectly by reversing local  growth - factor deficiency, and directly by improving wound contraction through  interaction with the extracellular  matrix. The decrease in wound size  might  have the potential to offset diabetic - related wound - healing impairment  significantly.
                                                 

       In a  randomized  controlled  trial in 28 diabetic patients with critical limb ischemia, Huang et al reported improvement in limb ischemia and foot ulcers.  By far the most studies of cell therapy have used intramuscular implantation method or intraarterial  injection. Progenitor cell- based  therapy may have great clinical potential.

TISSUE ENGINEERING


   Tissue engineering may allow the patients 's own cells to be obtained and seeded onto bio- degradable scaffolds that permit the formation of a particular tissue. These tissues can be employed to repair tissue defects caused by disease of trauma. Furthermore, tissue engineering may allow the ex- vivo engineering of tissue by means of  three- dimensional  bioscaffolds seeded  with mature cell or stem cells and cultivation in bioreactors leading to the formation of whole tissues or organs, e.g, liver, heart, cartilage, e.t.c .
    MSCs are good candidates for tissue engineering protocols . Several  scaffolds are currently available and may be classified as biologically derived polymers isolated from extracellular matrix, plants, seaweeds (e.g. hydroxyapatite, tricalcium phosphate, polyactide and polyglycolide) or a combination of both.
     Mesenchymal  stem cells (MSCs)  are characterized by their capacity  for self- renewal and the production of multiple lineages whereas MSCs exist in many other tissues, e.g. skeletal muscle, fat, spinal membrane.
   Embryonic stem cells offer higher pluripotency but remain problematic in clinical use because of ethical issues. In contrast MSCs harvested from adult organisms are ethically uncomplicated and readily available. However , the harvesting of these cells requires  invasive procedures and adult MSCs have poor quality when compared with embryonic stem cells (Baxter et al, 2004; Roura et al, 2006. )
                                                             

    Stem cells with fetal origins have the potential to offer the ideal balance between quality and ethics. Fetal cells from fetal tissue such as umbilical cord, umbilical cord blood or placenta  may  lie in between (Embryonic  and adult ) with respect  to quality and quantity.
     This is an attractive source for clinical applications and more studies should be carried out.
     Polyglycolic  acid nonwoven mesh tubes coated with copolymer solution were seeded with autologous bone marrow derived mononuclear  cells and a living autologous  vascular graft with growth  potential  developed . This is for advancing the field of congenital heart surgery..The currently available synthetic vascular grafts such as PTF  lack growth potential  and present problems related  to biocompatibility including thrombosis , ectopic  calcification and increased susceptibility to infection.
    Due to lack of growth potential  the surgery  needs to be delayed until the patient recipient has grown to a suitable  size to allow for inflammation  of an adult  size graft.
   Tissue engineered graft in the surgical repair of congenital anomalies is cearly  established.
    Mesenchymal  stem cells are an attractive cell source for regenerative  medicine.
      Bone marrow aspirate is obtained from the iliac crest. Synovium is harvested  from the knee joint. Adipose tissue can  be harvested from perinephric  fat tissue. Muscle was harvested  from anterior  tibial muscles.
     Cells from various sources were studied. Synovium and muscle derived cells had a higher  proliferation potential than bone marrow and adipose derived cells.. The  earlier  types had much more chondrogenic potential.
     Transplanting autologous chondrocytes  cultured in collagen  gel has been reported  for the treatment of full thickness  defects  of cartilage.
     Neovascularisation  is a critical step in tissue engineering applications, since implantation of voluminous  grafts without  sufficient vascularity results in hypoxic cell death  of central  tissues. A three dimensional  spheroidal co culture system consisting of human  umbilical vein  endothelial  cells have been developed to improve angiogenesis in tissue engineering.  Human  umbilical vein endothelial  capillary grown in collagen  gels are able to form luminized  capillary like structures and there is stimulatory effect of fibroblasts on endothelial cell sprouting .


Cell Therapy For Spinal Cord Injury


  Spinal   cord injury has no curative therapy at present . For a future efficient treatment one has to consider and combine the following approaches :
1. Tissue or cell transplantation ,
2. Providing growth stimulating factors. There is direct  disruption  of nerve tracts with secondary  damage done to oestemia and  hemorrhage. The glial scar forms at the site and is a barrier for future representations of the brain .
    
   Therefore in the acute setting, secondary damage is linked by decompression of the  spinal cord by laminectomy  to limit ischemia, orthopaedic fixation of the  involved  vertebrae  and high dose of steroids.
    
    Currently, the existence of endogenous mechanisms for neural  regeneration is being  accepted. In multiple  animal studies the presence of neural  stem cells in different areas of brain has been . Uchida et al have documented the existence  of adult neural stem cells in the subventricular zones of the brain .


      During the last decade,

multiple attempts in animal  models of spinal cord injury have been investigated. The approaches have focused  on  I) replacement  of damaged  neural tissue, II) enhancement  of endogenous  neural  regeneration , III) modulation of inflammatory  response  after spinal cord injury .
       
     Mc Donald et al differentiated murine embryonic stem cells into neural progenitor cells and transplanted these  cells into a rat model of spinal cord injury with success. Transplantation of adult neural  stem cells isolated post-mortem out of human brains was associated with extensive remyelination comparable with myelination pattern  of Schwann's cells in the peripheral  nervous system, when transplanted in the demyelinated rat spinal cord.

         Others reported improvement after transplantation of murine neural stem cells embedded in a polymer scaffold  in a hemi section model in rat. Despite all the above success with cell therapy , immunological rejection has to be noted.
     
    To circumvent this problem of rejection MSCs residing in bone marrow have received much attention. These can be cultured easily out of bone marrow and in vitro have shown trans- differentiation into neural cells .
    
    After transplantation into brain and spinal cord their differentiation into cells with neuronal and astrocyte characteristics was reported.
      
     Olfactory ensheathing cells have been extracted in humans and their transplantation has improved motor and sensory recover after spinal cord injury.
      
     These results are encouraging and the autologous nature has the relative ease of obtaining these cells and is a good therapeutic  treatment  for spinal injury.


Thursday, October 15, 2015

Diabetic Retinopathy

Diabetic  Retinopathy


Discussion
   Diabetic retinopathy  is the most  common cause  of newly diagnosed legal blindness amongst  the working  population  in the  industrialized  world today. . Although majority  of diabetic patients have retinopathy of varying severity, approximately 25% of the  diabetic patients have sight - threatening diabetic  retinopathy which  leads  to legal  blindness  (best corrected visual acuity of 20/200 or worse ).  Blindness  due to retinopathy  is 25 times more common in the diabetic, when  compared to the non diabetic population.
    Approximately 10 % of the  diabetic  population has type  1 (insulin- dependent) diabetes mellitus, which is usually diagnosed before  the age of 30 years. The majority (90%) of diabetic patients, however have type 2 ( non- insulin- dependent )  diabetes mellitus, which is diagnosed after the age of 30 years. Diabetic retinopathy is a highly specific vascular  complication of both type 1 and type 2  diabetes mellitus, and the duration  of diabetes  is a significant risk factor for the development  of retinopathy.
   Macular oedema  represents  a common pathologic  sequel of the  retina associated  with a  broad spectrum  of potential  insults. Diabetic macular oedema (DME) can occur at virtually  any  stage during  diabetic  retinopathy  development , and it represents  the leading  cause of visual  impairment in people with diabetes.  One of the most common  causes of  macular oedema is diabetes mellitus, and it is the cause  of visual loss in the latter.  The duration of macular oedema could be an  important  factor for visual prognosis.

   Molecular  basis  of  diabetic retinopathy . The retinal changes in patients  with diabetes resulted from five fundamental processes:
I)  the  formation of retinal  capillary  micro aneurysms, The development
II) the development  of excessive vascular permeability,
III)  vascular  occlusion ,
IV) the proliferation  of new blood vessels and accompanying  fibrous tissue on  the  surface  of the retina  and  optic disk, and
V )  the  contraction of these  fibro vascular proliferations and the  vitreous.
   
  The  clinic pathological lesions  of diabetic  retinopathy have been  well  classified. Although a  multitude of pathogenic  mechanisms  have  been   proposed, the underlying  dysfunctional   biochemical and molecular  pathways that lead to  initiation and  progression  of DR still remains an enigma. Currently  four  major  biochemical  pathways  have been  hypothesized  to explain  the mechanism  of diabetic  eye diseases all starting initially from  hyperglycaemia  induced  vascular injury. These  mainly  include:

I) enhanced  glucose  flux through  the  polygon pathway,
II)  increased  intracellular  formation of advanced glycation  end- products (AGE),
 III )  activation of protein  Kinase C (PKC) is forms, and
IV)  stimulation of the  hexosamine pathway.
   
   Studies have suggested that  these  mechanisms  seem  to reflect  a hyperglycaemia  induced process initiated by superoxide  overproduction  by  mitochondrial  electron transport  chain. Studies  have shown that poor glycaemia  control and higher levels  of HbA 1 c are among the risk  factors for  the onset of DME.  The  Wisconsin Epidemiologic Study  of  Diabetic Retinopathy  found rates  progression to DME of 26% in patients with diabetes  for 14 Years  and 29 % at  20 years or longer after diagnosis.


  Diabetic  retinopathy (DR) is a  very  common , potentially preventable, long - term complication of type  1 diabetes and the leading cause of  acquired  loss of vision among working - age adults in  Europe  and North America. Most  vision loss  in diabetes is a  result  of  diabetic macular  oedema, which  results  after  breakdown of the blood retinal barrier. Diabetic  macular  oedema is the  result  of retinal  micro vascular changes that occur  in patients with diabetes.  Thickening  of the basement membrane  and  reduction  in the number  of  pericytes is  believed to lead  to  increased  permeability  and  incompetence of

retinal  vasculature.  This  compromise  of the  blood- retinal  barrier  leads  to the leakage  of  plasma  constituents in  the  surrounding  retina,  resulting  in retinal  oedema.  The  hypoxic  state  achieved  through  this  mechanism can also stimulate the production of vascular endothelial  growth  factor (VEGF).  Macular  oedema affects approximately 29% of patients with diabetes  who have  disease  duration  of 20 years  or longer  and  constitutes the primary  cause  of visual  impairment  in  this  population.  For 30  years  the standard  of  treatment  has been  glycaemia  control  and  photocoagulation.  Despite  this,  some patients  suffer  permanent  visual  loss  even  after  intensive  treatment.  Despite  intensive  study,  current  understanding  of the  pathogenesis  of  diabetic  macular  oedema  remains  incomplete.  Hyperglycaemia  is clearly  the  strongest  known risk  factor for  DR.  Nevertheless,  whereas  intensive  glucose  lowering  was  effective  in  substantially  reducing  the  incidence  and  progression  of  retinopathy  in  the  Diabetes  Control  and  Complication  Trial (DCCT), there  was no  statistically  significant  effect  on the  incidence  of clinically  significant  macular oedema (CSME) during  the trial.  Thus, other  factors are  likely  to  play  at least  a contributory  role  in the  pathogenesis of CSME.

End - Stage Kidney Disease

End - Stage Kidney Disease

     End- stage kidney disease is the final stage of chronic kidney disease (CKD), which is also known as chronic   renal  disease (CRD).  This  final  stage, stage 5 CKD, is also known  as chronic kidney failure (CKF), chronic renal failure (CRF) or end stage renal disease (ESRD). Chronic  kidney  disease is a progressive  loss of kidney function  (renal function ) that  continues over a span of months to years, through  the five stages. The  progressive of the  kidney disease is measured  by the lowering  of the  glomerular  filtration  rate (GFR). This is usually  measured  by the  level  of  creatinine  in the patient's  bloodserum. Patients  with  a GFR of less than  60 mL /min/1.73 m are  considered  to have  chronic  kidney disease, regardless  of whether  kidney damage is present and noticed . At  this  level, the GFR is already lowered  by at least half of the normal adult level of healthy kidney function.
     Chronic renal failure(CRF) requiring dialysis or transplantation is known as end- stage renal disease  (ESRD). In the  United  States, diabetic nephropathy is the most common and hypertension   the second  most common  cause.  Along  with  glomerulonephritis, these  cause  approximately 75% of all  adult cases. Certain  geographic  areas  have  a high incidence  of HIV  nephropathy.  Genetic  kidney disease such  as  polycystic  kidney disease is a common  cause in young  adults.  Patients with end- stage renal disease (ESRD)  are  commonly encountered in the emergency departments (ED) with  problems  related  to the  metabolic  complications  of their  renal disease  or dialysis complications.  Various  problems related to vascular access in patients on hemodialysis  and to  abdominal catheters in patients  using continuous  ambulatory  peritoneal  dialysis(CAPD)  are also common. Patients  who have undergone renal  transplantation  may experience a  variety of transplant- related conditions.
   All  major organ systems  are affected  by renal  failure. Prevalence of symptoms is a function of the  glomerular  filtration  rate (GFR) , which  averages  120 mL / min in a healthy  adult.  As the GFR  falls to  less  than  approximately 20% of normal, symptoms of uremia may begin to occur. They almost are invariably  present  when  the GFR decrease to less than 10% of normal. Measuring  GFR  requires a  timed  urine collection as well as measurement  of serum  creatinine. However, it  can be  accurately  estimated  from   a  patient's age,  weight,  gender, and  serum  creatinine  level.
   Signs and  symptoms of  renal  faiure  are due to overt  metabolic  derangements  resulting from inability of failed kidneys to regular  electrolyte, fluid, and acid- base balance, they are also due to  accumulation  of toxic products of amino acid metabolism in the serum.


INCIDENCE  AND  PREVALENCE

      During  2004, the last year with  complete data availability , 104,364 patients (approximately 0.03% of the  US population )  began renal replacement  therapy, an adjusted  incidence rate of 339 per 1,000,000 . As  of 2005 , more than 485,000 patients were receiving treatment for ESRD in the United States . As a result, patients with ESRD are encountered on a regular  basis in US emergency departments .

International

    The  morbidity and mortality of dialysis  patients is much  higher in the United States  compared  with most other countries.  This  is probably a consequence of selection  bias.  Due to liberal  criteria for receiving  government - funded  dialysis  in the  United States  and  rationing  (both medical and economic )  in most other countries, US patients receiving dialysis  are on the  average  older and sicker than those in  other countries .

Mortality / Morbidity

 Patients in renal failure  are  prone  to all of the  complications  of any underlying condition, such as diabetes and hypertension .  In  addition,  renal failure causes a variety of metabolic  and  physiologic  derangements .
   The most  common  cause of sudden  death in patients with end- stage  renal disease (ESRD) is  hyperkalemia , which is often  encountered  in  patients  after  missed  dialysis  or dietary  indiscretion .  Serum  potassium  also  rises  when the serum is acidemic, even though  total  body  potassium  is unchanged .  Hyperkalemia  is usually asymptomatic and should  be  treated  empirically  when  suspected  and  when  arrhythmia  or cardiovascular  compromise  is present .
- Iatrogenic  complications  related  to  fluid  administration  (fluid  overload)  or  medications  are  frequently  encountered  in  patients  in  renal  failure .
-  Cardiovascular  mortality  is 10-20 times  higher in dialysis  patients than in the  normal population .
-  Anemia  results  in  fatigue  reduced  exercise  capacity,  decreased  cognition, and  impaired  immunity .
-  Renal  transplant  patients  are  prone  to  infection ,  especially  in  the  immediate  post- transplant  period .

Race

 Etiology  of end- stage  renal  disease  (ESRD)  differs among  racial  groups  primarily  because  of the prevalence  of  predisposing conditions, such as  diabetes and  hypertension. In  populations with  problematic  access  and  utilization of  primary  medical  care  for treatment  of   predisposing  conditions,  ESRD  often  is  encountered  in  relatively  young  patients.  Diseases  such  as  diabetes and hypertension  are much less likely  to lead  to renal  failure  when  appropriately  treated . The cost  of primary  care  for  these  conditions is  far  lower  than for  dialysis or  transplantation, yet  primary  care  remains  poorly  funded,  while  ESRD  treatment  is  reimbursed  completely  by the  government .
  In the  United States , racial  and  ethnic  discrepancies in  ESRD  exist, with 2006 rates in  the  African  American  and  Native  American  populations 3.6 and  1.8 times greater, respectively,  than  the rate among  whites, and  the  rate  in  the Hispanic  population 1.5 times  higher than  of  non- Hispanics

Sex

 Presentation  and  treatment  of  chronic  renal  failure (CRF) and end- stage renal disease (ESRD)  do not differ  significantly  between  men  and  women . Differences  in causes  of renal  failure  are  related  to the  types of  underlying  conditions  prevalent  in men  and  women.

Age

While  the  etiology  of  CRF  differs  among age  groups, the presentations and  nature of  complications  are  similar.  Young  children  with  ESRD  often  are  treated  with  transplantation  rather  than  dialysis  because  of a  relatively greater long- term  benefit  compared  to that  of adults, and  due  to  difficulties  related  to  vascular  access  for  dialysis .

.